Uvulopalatopharyngoplasty and barbed reposition pharyngoplasty with and without hyoid suspension for obstructive sleep apnea hypopnea syndrome: A comparison of long-term functional results
Abstract
Obstructive sleep apnea hypopnea syndrome (OSAHS) is a common condition; when conservative approaches are not effective, surgical techniques aimed at reducing the airway obstruction effect are used. This retrospective study aimed at comparing the functional outcomes in patients with OSAHS undergoing uvulopalatopharyngoplasty (UPPP) according to Fairbanks and barbed reposition pharyngoplasty (BRP) according to Mantovani, with or without hyoid suspension (HS). One-hundred twenty-two consecutive OSAHS patients who underwent surgical treatment were included in the study. Patients were divided into 4 groups; all patients underwent preoperative and postoperative polysomnography (PSG) with apnea/hypopnea index (AHI) and oxygen desaturation index (ODI) evaluation, and Epworth Sleepiness Scale (ESS) evaluation. The results were analyzed according to the different surgical procedures in relation to the preoperative PSG and anthropometric data. A significant reduction was observed at 18-month follow-up for patients in BRP group for body mass index (p = 0.004), ESS (p < 0.0001), ODI (p < 0.0001), and AHI (p < 0.0001). Risk factors for poor postoperative AHI reduction were evaluated; preoperative AHI was the strongest independent protective factor, while preoperative ODI was the strongest risk factor. The association of HS with UPPP or BRP showed significant results in terms of higher postoperative AHI reduction only when associated to UPPP (p < 0.0001). This study showed that the BRP technique was more effective compared to UPPP for patients with OSAHS. The association of HS showed greater benefits in UPPP compared to BRP. Randomized prospective trials with longer follow-up are necessary to confirm our results and formulate a more accurate indication of the optimal therapeutic strategy.
Keywords
Obstructive sleep apnea hypopnea syndrome uvulopalatopharyngoplasty barbed reposition pharyngoplasty surgeryFull text
Introduction
Obstructive sleep apnea hypopnea syndrome (OSAHS) is a common condition affecting 23.4% of women and 49.7% of men over 40 years old [1,2]. The risk factors include age, male gender, cigarette smoking, obesity, and abnormal facial anatomy [3,4]. The clinical symptoms are excessive daytime sleepiness [5-7], morning headache [8], decrease of cognitive performance [9,10], sexual dysfunction [11], decreased quality of life [12-16], and increased cardiovascular risk [17-20].
The main pathological event of OSAHS is the collapse of the upper airways that may occur at the same time at different levels, such as nasal, retropalatal and/or retrobasilingual and/or laryngeal [21]. However, the most frequent site of collapse is the soft palate, followed by the pharyngeal walls, base of the tongue and palatine tonsils. The larynx, and especially the epiglottis, is less involved [22].
The primary management of OSAHS relies on conservative approaches such as improved sleep hygiene, weight loss, use of dental splints, and continuous positive airway pressure (CPAP) treatment [23-27]. CPAP has been first used to maintain the patency of the upper airways during sleep by Sullivan et al. in 1981 [28]; their results were confirmed by several follow-up studies and CPAP now represents the gold standard for OSAHS treatment. However, nearly 40% of patients show an intolerance to CPAP machine and require alternative treatments, including surgery [29,30].
Surgical techniques for OSAHS aim at reducing the airway obstruction effect due to the excessive bulk of soft tissues lining the rhino-oro-hypopharynx, and they may be performed as single or combined procedures and traditional or robot-assisted, depending on patient conditions [31-36]. The most common surgical procedure for OSAHS is uvulopalatopharyngoplasty (UPPP), first described by Fujita in 1984 [37] and subsequently standardized by Fairbanks in 1999 [38]. UPPP is used to treat the retropalatal region; however, it only treats obstruction in the soft palate, while it does not address the collapse at different levels. Simple UPPP as a treatment of OSAHS has a success rate that ranges between 16% and 83% [39-41]. Furthermore, the recurrence rate of OSAHS at 10 years is as high as 40%, especially in obese patients [42,43]. To overcome these limits of UPPP, Mantovani et al. [44] proposed in 2012 a new surgical technique, the barbed reposition pharyngoplasty (BRP), which laterally and anteriorly displaces the posterior pillar to enlarge the oropharyngeal inlet and the retropalatal space [22].
This retrospective study aimed at comparing the functional outcomes in patients with OSAHS undergoing UPPP according to Fairbanks and BRP according to Mantovani, with or without hyoid suspension (HS).
Materials and methods
One-hundred twenty-two consecutive patients with a definitive diagnosis of OSAHS who underwent surgical treatment between January 2015 and December 2018 in the Otolaryngology unit of our University hospital were included in this retrospective study. All patients signed a written informed consent; the procedures were performed in accordance with the standards of the ethics committee on human experimentation of our University Department that specifically approved this study, and in accordance with the Helsinki Declaration.
The inclusion criteria were age between 25 and 75 years, body mass index (BMI) >15 and <35, any degree of tonsillar volume, apnea-hypopnea index (AHI) >15, and failure of preoperative CPAP treatment.
The exclusion criteria were patients with severe medical conditions, patients with craniofacial anomalies that had affected airways, patients with limited mouth opening, prior airway surgery, and patients with the American Society of Anesthesiologists (ASA) physical status score >2.
All patients underwent preoperative otolaryngology clinical evaluation, endoscopic examination with Mueller maneuver, polysomnography (PSG) with AHI and oxygen desaturation index (ODI) evaluation, and Epworth sleepiness scale (ESS) evaluation. Clinical information, including age and gender, smoking history and comorbidities, were collected at the first visit for each patient.
Surgery was performed by the same surgeon using UPPP according to Fairbanks or the BRP technique according to Mantovani. The two procedures were performed alone or combined with HS, a hypopharyngeal procedure that allows lateral traction of the hypopharynx and moderate advancement of the base of the tongue.
Patients were subsequently divided into two groups based on the surgical procedure, group A: UPPP; group B: BRP.
Otolaryngology examination, PSG, and ESS were repeated in all patients 18 months after surgery. At follow-up visit, patients were classified based on PSG results as recovery (AHI<5, ESS<10, both reduced >50%), success (AHI<20, ESS <10, both reduced >50%), and failure (AHI>20, ESS>10, both reduced <50%).
Results were analyzed according to the different surgical procedures in relation to the preoperative PSG (AHI, ODI) and anthropometric (BMI) data.
Statistical analysis
Continuous variables were reported as medians and interquartile ranges (IQR). Dummy variables were reported as numbers and percentages. Mann–Whitney U test and Fisher’s exact test were used for comparisons of categorical and continuous variables. A multivariable logistic regression model was built with the intent to identify the risk factors for poor postoperative decreasing of AHI score. We defined as poor a decrease >50% after surgery, according to the definition by Rashwan et al. [45]. Seven different covariates were initially investigated in the model: age, gender, BRP as a surgical approach, and preoperative values of BMI, ESS, ODI, and AHI. A backward Wald method was used for the construction of the final model. Odds ratios (OR), standard errors (SE), and 95% confidence intervals (95% CI) were reported. Model fitting was tested adopting the Hosmer–Lemeshow test. A p < 0.05 was defined for significance. We used IBM SPSS Statistics for Windows, Version 24.0 (IBM Corp., Armonk, NY, USA).
Results
Comparison between UPPP and BRP groups
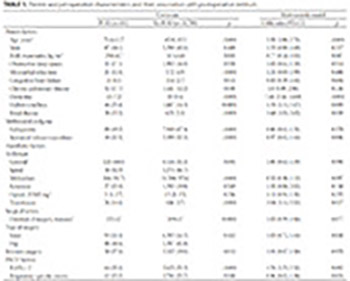
Demographics and postoperative course of patients that underwent UPPP and BRP are reported in Table 1. No significant differences were found between the two groups for age (p = 0.5), gender (p = 0.1), and contemporaneous HS procedure (p = 1.0). Similarly, preoperative ESS (p = 0.5) and ODI (p = 0.3) did not significantly differ. BRP cases had a higher preoperative BMI value compared to subjects in the UPPP group (p < 0.0001). Interestingly, all the preoperative variables significantly improved postoperatively in the BRP group. In this group, a significant reduction was observed for median delta BMI (p = 0.004), median delta ESS (p < 0.0001), ODI (p < 0.0001), and AHI (p < 0.0001). Only one patient (2.4%) in the BRP group showed a postoperative AHI reduction <50%, while 36 (45.0%) cases were reported in the UPPP group (p < 0.0001). Postoperative values of AHI, ODI, and ESS in the two groups are shown in Figure 1.
Risk factors for poor postoperative AHI reduction
A multivariable logistic regression model was constructed aimed to identify the prognostic variables for poor postoperative AHI reduction (defined as <50%), and three independent covariates were identified. The results are shown in Table 2.
Preoperative AHI value was the strongest independent protective factor, with an OR = 0.5 (95% CI = 0.4–0.7; p < 0.0001), indicating that the higher the preoperative AHI value, the lower the risk of experiencing a poor postoperative AHI decrease, with a 50% risk reduction for each unit increase in the preoperative AHI values. In addition, the surgical procedures BRP and HS were independent protective factors, with ORs = 0.05 (95% CI = 0.005–0.6; p = 0.02) and 0.07 (95% CI = 0.005–0.96; p = 0.047), respectively. In other terms, undergoing a BRP or a HS corresponded to a 95% and a 93% reduction in the risk of experiencing a postoperative poor AHI reduction value, respectively.
The preoperative ODI value was a significant risk factor for poor postoperative AHI reduction (OR = 1.9, 95% CI = 1.4–2.5; p < 0.0001); this indicates that the higher the preoperative ODI value, the higher the risk of poor postoperative AHI reduction.
Role of HS in combination with UPPP and BRP
According to the results observed in the multivariable model, in which HS had a positive role in reducing the risk of poor postoperative AHI reduction, a sub-analysis was performed aimed at identifying the combinatory effect of HS in the case of UPPP or BRP (Table 3). Interestingly, a substantial difference was observed when the sub-group of UPPP patients (n = 38) was compared with the other groups regarding postoperative AHI decreasing (p < 0.0001). The vast majority of cases treated only with UPPP showed a poor AHI decrease (n = 30; 78.9%), while the patients requiring a combinatory UPPP+HS treatment (n = 42) showed intermediate results (n = 6, 14.3%). Only one subject of poor AHI decrease was observed among the subjects treated with BRP (n = 20) or BRP+HS (n = 22).
Discussion
In the present study, we compared the functional outcomes of patients with OSAHS undergoing UPPP according to Fairbanks and BRP according to Mantovani. Our results show that BRP is more effective than UPPP; in fact, considering a similar value of the preoperatory AHI index, we found a greater decrease of postoperative AHI with the BRP technique compared to UPPP (10 vs. 16). A possible explanation is that BRP guarantees, compared to UPPP, a greater and more stable retraction of the pharyngeal soft tissue due to the latero-lateral traction and the anchorage to the pterygomandibular raphe, an enlargement of the anteroposterior space and better preservation of the mucosa and muscle tissue.
Our results also show that the efficacy of BRP in terms of AHI is not improved by HS. The UPPP surgical procedure, instead, showed a greater efficacy if performed with HS. The execution of HS reduces the latero-lateral hypopharyngeal collapse with the result of increasing the transverse diameters of the upper pharynx, optimizing in this way the action of the UPPP procedure. Contrarily, BRP guarantees an effective retropalatal enlargement without the necessity of HS. This is consistent with the results of previous studies [46].
Although some aspects of the pathophysiology of OSAS are still unknown, it has been widely accepted that pharyngeal obstruction during the apnea/hypopnea episodes derives from a complex set of anatomical and functional factors. OSAHS patients often present an obstruction at multiple levels of the upper airways and the sole execution of UPPP is frequently inadequate [41]. The most recent acquisitions in OSAHS surgery recommend to expand and stabilize the pharyngeal space; often, a satisfactory outcome is achieved with the combination of UPPP with other nasopharyngeal or oropharyngeal procedures. Riley et al. [47] proposed phase I multiple-level surgery for OSAHS patients using genioglossus advancement (GA) combined with HS. The development of new diagnostic procedures such as drug-induced sleep endoscopy (DISE) has allowed a better preoperative identification of the individual contribution of the different sites of obstruction. Nowadays, DISE is a fundamental procedure to plan a targeted and personalized surgical approach for each patient. At this regard, DISE allows to exclude from the traditional surgical procedures patients with OSAHS that originate from the collapse of the epiglottis due to hypertrophy of the tongue base, in which the reduction of the base of the tongue with robotic surgery has been shown to be more effective [48]. The advantages of robotic surgery are a good anatomical exposure of the surgical field, control of vascular and nervous structures, reduction of time of surgery, better aesthetic result, and improvement of quality of life.
The main limitation of our study is the relatively short follow-up (18 months); further studies with longer follow-up are necessary to confirm our findings.
Conclusion
This retrospective study showed that the BRP technique according to Mantovani was more effective, in the short term, compared to the classic UPPP technique of Fairbanks for patients with OSAHS. The combined use of HS showed greater benefits in UPPP compared to BRP. Randomized prospective trials with longer follow-up are necessary to confirm our results and formulate a more accurate indication of the optimal therapeutic strategy.
References
- Heinzer R, Vat S, Marques-Vidal P, Marti-Soler H, Andries D, Tobback N, et al. Prevalence of sleep-disordered breathing in the general population:The hypnolaus study. Lancet Respir Med 2015;3(4):310–8. https://doi.org/10.1016/s2213-2600(15)00043-0
- Sanna A, Lacedonia D. OSAS:Its burden increases, not enough the awareness. Multidiscip Respir Med 2018;13:42. https://doi.org/10.1186/s40248-018-0156-1
- Shie DY, Tsou YA, Tai CJ, Tsai MH. Impact of obesity on uvulopalatopharyngoplasty success in patients with severe obstructive sleep apnea:A retrospective single-center study in Taiwan. Acta Otolaryngol 2013;133(3):261–9. https://doi.org/10.3109/00016489.2012.741328
- Young T, Palta M, Dempsey J, Skatrud J, Weber S, Badr S. The occurrence of sleep-disordered breathing among middle-aged adults. N Engl J Med 1993;328(17):1230–5. https://doi.org/10.1056/nejm199304293281704
- Dongol EM, Williams AJ. Residual excessive sleepiness in patients with obstructive sleep apnea on treatment with continuous positive airway pressure. Curr Opin Pulm Med 2016;22(6):589–94. https://doi.org/10.1097/mcp.0000000000000324
- Maspero C, Giannini L, Galbiati G, Rosso G, Farronato G. Obstructive sleep apnea syndrome:A literature review. Minerva Stomatol 2015;64(2):97–109.
- Wang Q, Zhang C, Jia P, Zhang J, Feng L, Wei S, et al. The association between the phenotype of excessive daytime sleepiness and blood pressure in patients with obstructive sleep apnea-hypopnea syndrome. Int J Med Sci 2014;11(7):713–20. https://doi.org/10.7150/ijms.7487
- Spalka J, Kedzia K, Kuczynski W, Kudrycka A, Malolepsza A, Bialasiewicz P, et al. Morning headache as an obstructive sleep apnea-related symptom among sleep clinic patients-a cross-section analysis. Brain Sci 2020;10(1):57. https://doi.org/10.3390/brainsci10010057
- Karimzadeh F, Nami M, Boostani R. Sleep microstructure dynamics and neurocognitive performance in obstructive sleep apnea syndrome patients. J Integr Neurosci 2017;16(2):127–42. https://doi.org/10.3233/jin-170004
- Onen F, Onen H. Obstructive sleep apnea and cognitive impairment in the elderly. Psychol Neuropsychiatr Vieil 2010;8(3):163–9. https://doi.org/10.1684/pnv.2010.0219
- Santos T, Drummond M, Botelho F. Erectile dysfunction in obstructive sleep apnea syndrome-prevalence and determinants. Rev Port Pneumol 2012;18(2):64–71. https://doi.org/10.1016/j.rppnen.2012.01.002
- Silva GE, Goodwin JL, Vana KD, Quan SF. Obstructive sleep apnea and quality of life:Comparison of the SAQLI, FOSQ, and SF-36 questionnaires. Southwest J Pulm Crit Care 2016;13(3):137–49. https://doi.org/10.13175/swjpcc082-16
- Isidoro SI, Salvaggio A, Lo Bue A, Romano S, Marrone O, Insalaco G. Effect of obstructive sleep apnea diagnosis on health related quality of life. Health Qual Life Outcomes 2015;13:68. https://doi.org/10.1186/s12955-015-0253-1
- Moyer CA, Sonnad SS, Garetz SL, Helman JI, Chervin RD. Quality of life in obstructive sleep apnea:A systematic review of the literature. Sleep Med 2001;2(6):477–91. https://doi.org/10.1016/s1389-9457(01)00072-7
- Lacasse Y, Godbout C, Series F. Health-related quality of life in obstructive sleep apnoea. Eur Respir J 2002;19(3):499–503. https://doi.org/10.1183/09031936.02.00216902
- Passali GC, Ralli M, Galli J, Calo L, Paludetti G. How relevant is the impairment of smell for the quality of life in allergic rhinitis?. Curr Opin Allergy Clin Immunol 2008;8(3):238–42. https://doi.org/10.1097/aci.0b013e3282ffd6bb
- Iannella G, Vicini C, Colizza A, Meccariello G, Polimeni A, Greco A, et al. Aging effect on sleepiness and apneas severity in patients with obstructive sleep apnea syndrome:A meta-analysis study. Eur Arch Otorhinolaryngol 2019;276(12):3549–56. https://doi.org/10.1007/s00405-019-05616-0
- Fava C, Montagnana M, Favaloro EJ, Guidi GC, Lippi G. Obstructive sleep apnea syndrome and cardiovascular diseases. Semin Thromb Hemost 2011;37(3):280–97. https://doi.org/10.1055/s-0031-1273092
- Lu D, Li N, Yao X, Zhou L. Potential inflammatory markers in obstructive sleep apnea-hypopnea syndrome. Bosn J Basic Med Sci 2017;17(1):47–53. https://doi.org/10.17305/bjbms.2016.1579
- Kruthiventi SC, Kane GC, Sprung J, Weingarten TN, Warner ME. Postoperative pulmonary complications in contemporary cohort of patients with pulmonary hypertension. Bosn J Basic Med Sci 2019;19(4):392–9. https://doi.org/10.17305/bjbms.2019.4332
- Bhutada AM, Broughton WA, Garand KL. Obstructive sleep apnea syndrome (OSAS) and swallowing function-a systematic review. Sleep Breath 2020. Online ahead of print
- Vicini C, Hendawy E, Campanini A, Eesa M, Bahgat A, AlGhamdi S, et al. Barbed reposition pharyngoplasty (BRP) for OSAHS:A feasibility, safety, efficacy and teachability pilot study. We are on the giant's shoulders. Eur Arch Otorhinolaryngol 2015;272(10):3065–70. https://doi.org/10.1007/s00405-015-3628-3
- Luzzi V, Ierardo G, Di Carlo G, Saccucci M, Polimeni A. Obstructive sleep apnea syndrome in the pediatric age:The role of the dentist. Eur Rev Med Pharmacol Sci 2019;23(1):9–14. https://doi.org/10.26355/eurrev_201903_17341
- De Benedetto M, Arigliani M, Ballacchino A, Cassano P, Toraldo DM, Ralli M, et al. Obstructive sleep apnea syndrome in the pediatric age:The role of the otorhinolaryngologist. Eur Rev Med Pharmacol Sci 2019;23(1):3–8. https://doi.org/10.26355/eurrev_201903_17340
- Toraldo DM, Di Michele L, Ralli M, Arigliani M, Passali GC, De Benedetto M, et al. Obstructive sleep apnea syndrome in the pediatric age:The role of the pneumologist. Eur Rev Med Pharmacol Sci 2019;23(1):15–8. https://doi.org/10.26355/eurrev_201903_17342
- Yu K, Jiang ZH, Zhang LG. Therapeutic effects of long-term continuous positive airway pressure treatment on improving leptomeningeal collateral circulation in obstructive sleep apnea syndrome patients. Eur Rev Med Pharmacol Sci 2018;22(13):4261–7. https://doi.org/10.26355/eurrev_201807_15422
- Sato K, Nakajima T. Review of systematic reviews on mandibular advancement oral appliance for obstructive sleep apnea:The importance of long-term follow-up. Jpn Dent Sci Rev 2020;56(1):32–7. https://doi.org/10.1016/j.jdsr.2019.10.002
- Sullivan CE, Issa FG, Berthon-Jones M, Eves L. Reversal of obstructive sleep apnoea by continuous positive airway pressure applied through the nares. Lancet 1981;1(8225):862–5. https://doi.org/10.1016/s0140-6736(81)92140-1
- Richard W, Venker J, den Herder C, Kox D, van den Berg B, Laman M, et al. Acceptance and long-term compliance of nCPAP in obstructive sleep apnea. Eur Arch Otorhinolaryngol 2007;264(9):1081–6. https://doi.org/10.1007/s00405-007-0311-3
- Kribbs NB, Pack AI, Kline LR, Smith PL, Schwartz AR, Schubert NM, et al. Objective measurement of patterns of nasal CPAP use by patients with obstructive sleep apnea. Am Rev Respir Dis 1993;147(4):887–95. https://doi.org/10.1164/ajrccm/147.4.887
- Tamaki A, Rocco JW, Ozer E. The future of robotic surgery in otolaryngology-head and neck surgery. Oral Oncol 2020;101:104510. https://doi.org/10.1016/j.oraloncology.2019.104510
- Bellucci R, Campo F, Ralli M, Buonopane C, Di Girolamo S, Passali D, et al. Obstructive sleep apnea syndrome in the pediatric age:The role of the anesthesiologist. Eur Rev Med Pharmacol Sci 2019;23(1):19–26. https://doi.org/10.26355/eurrev_201903_17343
- Li HY, Lee LA, Hsin LJ, Fang TJ, Lin WN, Chen HC, et al. Intrapharyngeal surgery with integrated treatment for obstructive sleep apnea. Biomed J 2019;42(2):84–92. https://doi.org/10.1016/j.bj.2019.02.002
- Veasey SC, Rosen IM. Obstructive sleep apnea in adults. N Engl J Med 2019;380(15):1442–9. https://doi.org/10.1056/NEJMcp1816152
- Vicini C, Montevecchi F. Transoral robotic surgery for obstructive sleep apnea:Past, present, and future. Sleep Med Clin 2019;14(1):67–72. https://doi.org/10.1016/j.jsmc.2018.10.008
- Li HY. Palatal surgery for obstructive sleep apnea:From ablation to reconstruction. Sleep Med Clin 2019;14(1):51–8. https://doi.org/10.1016/j.jsmc.2018.10.006
- Fujita S. UPPP for sleep apnea and snoring. Ear Nose Throat J 1984;63(5):227–35.
- Fairbanks DN. Operative techniques of uvulopalatopharyngoplasty. Ear Nose Throat J 1999;78(11):846–50. https://doi.org/10.1177/014556139907801108
- Carpenter JM, LaMear WR. Uvulopalatopharyngoplasty:Results of a patient questionnaire. Ann Otol Rhinol Laryngol 2008;117(1):24–6. https://doi.org/10.1177/000348940811700106
- Elshaug AG, Moss JR, Southcott AM, Hiller JE. Redefining success in airway surgery for obstructive sleep apnea:A meta analysis and synthesis of the evidence. Sleep 2007;30(4):461–7. https://doi.org/10.1093/sleep/30.4.461
- Sher AE, Schechtman KB, Piccirillo JF. The efficacy of surgical modifications of the upper airway in adults with obstructive sleep apnea syndrome. Sleep 1996;19(2):156–77. https://doi.org/10.1093/sleep/19.2.156
- Khan A, Ramar K, Maddirala S, Friedman O, Pallanch JF, Olson EJ. Uvulopalatopharyngoplasty in the management of obstructive sleep apnea:The Mayo Clinic experience. Mayo Clin Proc 2009;84(9):795–800. https://doi.org/10.4065/84.9.795
- Fujita S, Conway W, Zorick F, Roth T. Surgical correction of anatomic azbnormalities in obstructive sleep apnea syndrome:Uvulopalatopharyngoplasty. Otolaryngol Head Neck Surg 1981;89(6):923–34. https://doi.org/10.1177/019459988108900609
- Mantovani M, Minetti A, Torretta S, Pincherle A, Tassone G, Pignataro L. The velo-uvulo-pharyngeal lift or “roman blinds”technique for treatment of snoring:A preliminary report. Acta Otorhinolaryngol Ital 2012;32(1):48–53.
- Rashwan MS, Montevecchi F, Cammaroto G, Deen MB, Iskander N, El Hennawi D, et al. Evolution of soft palate surgery techniques for obstructive sleep apnea patients:A comparative study for single-level palatal surgeries. Clin Otolaryngol 2018;43(2):584–90. https://doi.org/10.1111/coa.13027
- Tetter N, Tschopp K. Contribution of hyoid and tonsillar procedures to outcome in multilevel surgery for obstructive sleep apnea syndrome. ORL J Otorhinolaryngol Relat Spec 2016;78(6):353–60. https://doi.org/10.1159/000458445
- Riley RW, Powell NB, Guilleminault C. Obstructive sleep apnea syndrome:A review of 306 consecutively treated surgical patients. Otolaryngol Head Neck Surg 1993;108(2):117–25. https://doi.org/10.1177/019459989310800203
- Vicini C, Dallan I, Canzi P, Frassineti S, La Pietra MG, Montevecchi F. Transoral robotic tongue base resection in obstructive sleep apnoea-hypopnoea syndrome:A preliminary report. ORL J Otorhinolaryngol Relat Spec 2010;72(1):22–7. https://doi.org/10.1159/000284352
About this article
Correspondence
* Corresponding author: Massimo Ralli, Department of Sense Organs, Sapienza University of Rome, Viale dell’Università 33, 00168 Rome, Italy. Phone: +390649976808. E-mail: [email protected]
Article history
Received: 2020-04-01 · Accepted: 2020-04-26
Conflicts of interest
Conflict of interest statement: The authors declare no conflict of interests
Copyright
Copyright: © The Author(s) (2021)
Downloads
References
Heinzer R, Vat S, Marques-Vidal P, Marti-Soler H, Andries D, Tobback N, et al. Prevalence of sleep-disordered breathing in the general population:The hypnolaus study. Lancet Respir Med. 2015;3(4):310-8. doi:10.1016/s2213-2600(15)00043-0 DOI: https://doi.org/10.1016/S2213-2600(15)00043-0
Sanna A, Lacedonia D. OSAS:Its burden increases, not enough the awareness. Multidiscip Respir Med. 2018;13:42. doi:10.1186/s40248-018-0156-1 DOI: https://doi.org/10.4081/mrm.2018.207
Shie DY, Tsou YA, Tai CJ, Tsai MH. Impact of obesity on uvulopalatopharyngoplasty success in patients with severe obstructive sleep apnea:A retrospective single-center study in Taiwan. Acta Otolaryngol. 2013;133(3):261-9. doi:10.3109/00016489.2012.741328 DOI: https://doi.org/10.3109/00016489.2012.741328
Young T, Palta M, Dempsey J, Skatrud J, Weber S, Badr S. The occurrence of sleep-disordered breathing among middle-aged adults. N Engl J Med. 1993;328(17):1230-5. doi:10.1056/nejm199304293281704 DOI: https://doi.org/10.1056/NEJM199304293281704
Dongol EM, Williams AJ. Residual excessive sleepiness in patients with obstructive sleep apnea on treatment with continuous positive airway pressure. Curr Opin Pulm Med. 2016;22(6):589-94. doi:10.1097/mcp.0000000000000324 DOI: https://doi.org/10.1097/MCP.0000000000000324
Maspero C, Giannini L, Galbiati G, Rosso G, Farronato G. Obstructive sleep apnea syndrome:A literature review. Minerva Stomatol. 2015;64(2):97-109.
Wang Q, Zhang C, Jia P, Zhang J, Feng L, Wei S, et al. The association between the phenotype of excessive daytime sleepiness and blood pressure in patients with obstructive sleep apnea-hypopnea syndrome. Int J Med Sci. 2014;11(7):713-20. doi:10.7150/ijms.7487 DOI: https://doi.org/10.7150/ijms.7487
Spalka J, Kedzia K, Kuczynski W, Kudrycka A, Malolepsza A, Bialasiewicz P, et al. Morning headache as an obstructive sleep apnea-related symptom among sleep clinic patients-a cross-section analysis. Brain Sci. 2020;10(1):57. doi:10.3390/brainsci10010057 DOI: https://doi.org/10.3390/brainsci10010057
Karimzadeh F, Nami M, Boostani R. Sleep microstructure dynamics and neurocognitive performance in obstructive sleep apnea syndrome patients. J Integr Neurosci. 2017;16(2):127-42. doi:10.3233/jin-170004 DOI: https://doi.org/10.3233/JIN-170004
Onen F, Onen H. Obstructive sleep apnea and cognitive impairment in the elderly. Psychol Neuropsychiatr Vieil. 2010;8(3):163-9. doi:10.1684/pnv.2010.0219
Santos T, Drummond M, Botelho F. Erectile dysfunction in obstructive sleep apnea syndrome-prevalence and determinants. Rev Port Pneumol. 2012;18(2):64-71. doi:10.1016/j.rppnen.2012.01.002 DOI: https://doi.org/10.1016/j.rppnen.2012.01.002
Silva GE, Goodwin JL, Vana KD, Quan SF. Obstructive sleep apnea and quality of life:Comparison of the SAQLI, FOSQ, and SF-36 questionnaires. Southwest J Pulm Crit Care. 2016;13(3):137-49. doi:10.13175/swjpcc082-16 DOI: https://doi.org/10.13175/swjpcc082-16
Isidoro SI, Salvaggio A, Lo Bue A, Romano S, Marrone O, Insalaco G. Effect of obstructive sleep apnea diagnosis on health related quality of life. Health Qual Life Outcomes. 2015;13:68. doi:10.1186/s12955-015-0253-1 DOI: https://doi.org/10.1186/s12955-015-0253-1
Moyer CA, Sonnad SS, Garetz SL, Helman JI, Chervin RD. Quality of life in obstructive sleep apnea:A systematic review of the literature. Sleep Med. 2001;2(6):477-91. doi:10.1016/s1389-9457(01)00072-7 DOI: https://doi.org/10.1016/S1389-9457(01)00072-7
Lacasse Y, Godbout C, Series F. Health-related quality of life in obstructive sleep apnoea. Eur Respir J. 2002;19(3):499-503. doi:10.1183/09031936.02.00216902 DOI: https://doi.org/10.1183/09031936.02.00216902
Passali GC, Ralli M, Galli J, Calo L, Paludetti G. How relevant is the impairment of smell for the quality of life in allergic rhinitis?. Curr Opin Allergy Clin Immunol. 2008;8(3):238-42. doi:10.1097/aci.0b013e3282ffd6bb DOI: https://doi.org/10.1097/ACI.0b013e3282ffd6bb
Iannella G, Vicini C, Colizza A, Meccariello G, Polimeni A, Greco A, et al. Aging effect on sleepiness and apneas severity in patients with obstructive sleep apnea syndrome:A meta-analysis study. Eur Arch Otorhinolaryngol. 2019;276(12):3549-56. doi:10.1007/s00405-019-05616-0 DOI: https://doi.org/10.1007/s00405-019-05616-0
Fava C, Montagnana M, Favaloro EJ, Guidi GC, Lippi G. Obstructive sleep apnea syndrome and cardiovascular diseases. Semin Thromb Hemost. 2011;37(3):280-97. doi:10.1055/s-0031-1273092 DOI: https://doi.org/10.1055/s-0031-1273092
Lu D, Li N, Yao X, Zhou L. Potential inflammatory markers in obstructive sleep apnea-hypopnea syndrome. Bosn J Basic Med Sci. 2017;17(1):47-53. doi:10.17305/bjbms.2016.1579 DOI: https://doi.org/10.17305/bjbms.2016.1579
Kruthiventi SC, Kane GC, Sprung J, Weingarten TN, Warner ME. Postoperative pulmonary complications in contemporary cohort of patients with pulmonary hypertension. Bosn J Basic Med Sci. 2019;19(4):392-9. doi:10.17305/bjbms.2019.4332 DOI: https://doi.org/10.17305/bjbms.2019.4332
Bhutada AM, Broughton WA, Garand KL. Obstructive sleep apnea syndrome (OSAS) and swallowing function-a systematic review. Sleep Breath. 2020. doi:10.1007/s11325-020-02037-w DOI: https://doi.org/10.1007/s11325-020-02037-w
Vicini C, Hendawy E, Campanini A, Eesa M, Bahgat A, AlGhamdi S, et al. Barbed reposition pharyngoplasty (BRP) for OSAHS:A feasibility, safety, efficacy and teachability pilot study. We are on the giant's shoulders. Eur Arch Otorhinolaryngol. 2015;272(10):3065-70. doi:10.1007/s00405-015-3628-3 DOI: https://doi.org/10.1007/s00405-015-3628-3
Luzzi V, Ierardo G, Di Carlo G, Saccucci M, Polimeni A. Obstructive sleep apnea syndrome in the pediatric age:The role of the dentist. Eur Rev Med Pharmacol Sci. 2019;23(1):9-14. doi:10.26355/eurrev_201903_17341
De Benedetto M, Arigliani M, Ballacchino A, Cassano P, Toraldo DM, Ralli M, et al. Obstructive sleep apnea syndrome in the pediatric age:The role of the otorhinolaryngologist. Eur Rev Med Pharmacol Sci. 2019;23(1):3-8. doi:10.26355/eurrev_201903_17340
Toraldo DM, Di Michele L, Ralli M, Arigliani M, Passali GC, De Benedetto M, et al. Obstructive sleep apnea syndrome in the pediatric age:The role of the pneumologist. Eur Rev Med Pharmacol Sci. 2019;23(1):15-8. doi:10.26355/eurrev_201903_17342
Yu K, Jiang ZH, Zhang LG. Therapeutic effects of long-term continuous positive airway pressure treatment on improving leptomeningeal collateral circulation in obstructive sleep apnea syndrome patients. Eur Rev Med Pharmacol Sci. 2018;22(13):4261-7. doi:10.26355/eurrev_201807_15422
Sato K, Nakajima T. Review of systematic reviews on mandibular advancement oral appliance for obstructive sleep apnea:The importance of long-term follow-up. Jpn Dent Sci Rev. 2020;56(1):32-7. doi:10.1016/j.jdsr.2019.10.002 DOI: https://doi.org/10.1016/j.jdsr.2019.10.002
Sullivan CE, Issa FG, Berthon-Jones M, Eves L. Reversal of obstructive sleep apnoea by continuous positive airway pressure applied through the nares. Lancet. 1981;1(8225):862-5. doi:10.1016/s0140-6736(81)92140-1 DOI: https://doi.org/10.1016/S0140-6736(81)92140-1
Richard W, Venker J, den Herder C, Kox D, van den Berg B, Laman M, et al. Acceptance and long-term compliance of nCPAP in obstructive sleep apnea. Eur Arch Otorhinolaryngol. 2007;264(9):1081-6. doi:10.1007/s00405-007-0311-3 DOI: https://doi.org/10.1007/s00405-007-0311-3
Kribbs NB, Pack AI, Kline LR, Smith PL, Schwartz AR, Schubert NM, et al. Objective measurement of patterns of nasal CPAP use by patients with obstructive sleep apnea. Am Rev Respir Dis. 1993;147(4):887-95. doi:10.1164/ajrccm/147.4.887 DOI: https://doi.org/10.1164/ajrccm/147.4.887
Tamaki A, Rocco JW, Ozer E. The future of robotic surgery in otolaryngology-head and neck surgery. Oral Oncol. 2020;101:104510. doi:10.1016/j.oraloncology.2019.104510 DOI: https://doi.org/10.1016/j.oraloncology.2019.104510
Bellucci R, Campo F, Ralli M, Buonopane C, Di Girolamo S, Passali D, et al. Obstructive sleep apnea syndrome in the pediatric age:The role of the anesthesiologist. Eur Rev Med Pharmacol Sci. 2019;23(1):19-26. doi:10.26355/eurrev_201903_17343 DOI: https://doi.org/10.1007/978-3-030-13269-9_1
Li HY, Lee LA, Hsin LJ, Fang TJ, Lin WN, Chen HC, et al. Intrapharyngeal surgery with integrated treatment for obstructive sleep apnea. Biomed J. 2019;42(2):84-92. doi:10.1016/j.bj.2019.02.002 DOI: https://doi.org/10.1016/j.bj.2019.02.002
Veasey SC, Rosen IM. Obstructive sleep apnea in adults. N Engl J Med. 2019;380(15):1442-9. doi:10.1056/NEJMcp1816152 DOI: https://doi.org/10.1056/NEJMcp1816152
Vicini C, Montevecchi F. Transoral robotic surgery for obstructive sleep apnea:Past, present, and future. Sleep Med Clin. 2019;14(1):67-72. doi:10.1016/j.jsmc.2018.10.008 DOI: https://doi.org/10.1016/j.jsmc.2018.10.008
Li HY. Palatal surgery for obstructive sleep apnea:From ablation to reconstruction. Sleep Med Clin. 2019;14(1):51-8. doi:10.1016/j.jsmc.2018.10.006 DOI: https://doi.org/10.1016/j.jsmc.2018.10.006
Fujita S. UPPP for sleep apnea and snoring. Ear Nose Throat J. 1984;63(5):227-35.
Fairbanks DN. Operative techniques of uvulopalatopharyngoplasty. Ear Nose Throat J. 1999;78(11):846-50. doi:10.1177/014556139907801108 DOI: https://doi.org/10.1177/014556139907801108
Carpenter JM, LaMear WR. Uvulopalatopharyngoplasty:Results of a patient questionnaire. Ann Otol Rhinol Laryngol. 2008;117(1):24-6. doi:10.1177/000348940811700106 DOI: https://doi.org/10.1177/000348940811700106
Elshaug AG, Moss JR, Southcott AM, Hiller JE. Redefining success in airway surgery for obstructive sleep apnea:A meta analysis and synthesis of the evidence. Sleep. 2007;30(4):461-7. doi:10.1093/sleep/30.4.461 DOI: https://doi.org/10.1093/sleep/30.4.461
Sher AE, Schechtman KB, Piccirillo JF. The efficacy of surgical modifications of the upper airway in adults with obstructive sleep apnea syndrome. Sleep. 1996;19(2):156-77. doi:10.1093/sleep/19.2.156 DOI: https://doi.org/10.1093/sleep/19.2.156
Khan A, Ramar K, Maddirala S, Friedman O, Pallanch JF, Olson EJ. Uvulopalatopharyngoplasty in the management of obstructive sleep apnea:The Mayo Clinic experience. Mayo Clin Proc. 2009;84(9):795-800. doi:10.4065/84.9.795 DOI: https://doi.org/10.4065/84.9.795
Fujita S, Conway W, Zorick F, Roth T. Surgical correction of anatomic azbnormalities in obstructive sleep apnea syndrome:Uvulopalatopharyngoplasty. Otolaryngol Head Neck Surg. 1981;89(6):923-34. doi:10.1177/019459988108900609 DOI: https://doi.org/10.1177/019459988108900609
Mantovani M, Minetti A, Torretta S, Pincherle A, Tassone G, Pignataro L. The velo-uvulo-pharyngeal lift or “roman blinds”technique for treatment of snoring:A preliminary report. Acta Otorhinolaryngol Ital. 2012;32(1):48-53.
Rashwan MS, Montevecchi F, Cammaroto G, Deen MB, Iskander N, El Hennawi D, et al. Evolution of soft palate surgery techniques for obstructive sleep apnea patients:A comparative study for single-level palatal surgeries. Clin Otolaryngol. 2018;43(2):584-90. doi:10.1111/coa.13027 DOI: https://doi.org/10.1111/coa.13027
Tetter N, Tschopp K. Contribution of hyoid and tonsillar procedures to outcome in multilevel surgery for obstructive sleep apnea syndrome. ORL J Otorhinolaryngol Relat Spec. 2016;78(6):353-60. doi:10.1159/000458445 DOI: https://doi.org/10.1159/000458445
Riley RW, Powell NB, Guilleminault C. Obstructive sleep apnea syndrome:A review of 306 consecutively treated surgical patients. Otolaryngol Head Neck Surg. 1993;108(2):117-25. doi:10.1177/019459989310800203 DOI: https://doi.org/10.1177/019459989310800203
Vicini C, Dallan I, Canzi P, Frassineti S, La Pietra MG, Montevecchi F. Transoral robotic tongue base resection in obstructive sleep apnoea-hypopnoea syndrome:A preliminary report. ORL J Otorhinolaryngol Relat Spec. 2010;72(1):22-7. doi:10.1159/000284352 DOI: https://doi.org/10.1159/000284352
Article files
Additional Files
Accepted 2020-04-26
Published 2021-06-01
Publication details
- Citation
- Vol. 21 No. 3 (2021), pp. 364-369
- Language
- EN
- Section
- New and Emerging Methods
- Categories
- Research articles, New and Emerging Methods
How to cite (Vancouver)
AM, Cialente F, Ralli M, Colizza A, Lai Q, Placentino A, et al. Uvulopalatopharyngoplasty and barbed reposition pharyngoplasty with and without hyoid suspension for obstructive sleep apnea hypopnea syndrome: A comparison of long-term functional results. Biomol Biomed. 2021;21(3):364-369. https://doi.org/10.17305/bjbms.2020.4724